Search This Blog

Thursday, February 3, 2022

188


This was originally published here, in French (link).
We provide this translation for your convenience. Practical aspects may differ where you live.


The Saint Darwin or the End of Darwin

By Charles-Edouard!

Of course, it's a bit ironic: after two millennia of Catholicism, we're still looking for God's hand in life's contingencies. Abrahamism, and by way of recursion, Adamism, holds that we are all descendants, according to the same model, of a single human ancestor. Darwin overturns this by making all beings, all species, descendants of different ancestors, in fact, each time a little. By recursion, there is then a common ancestor to all beings.

This is just as false as Abrahamism, but a little less so, and so revolutionary. Lamarck, in 1809, in his Philosophie zoologique, exposes the concept of evolution of species. Darwin exposes a mechanism. Since then, others have been elucidated, and recently, it has been thrown in our faces!

Baltimore, Montagnier and other Nobel Prize winners


The founding dogma of molecular biology, enunciated by Francis H. C. Crick (Nobel Laureate), is that the information contained in genes is always transmitted unidirectionally from DNA to RNA (and then to proteins) and cannot be transmitted in the opposite direction. By dismissing the possibility of the RNA of SARS being written into the chromosomes, the propagandists fell in line with the dogma. Which had been invalidated by... David Baltimore (Nobel Prize winner for this discovery) and Dubelco (also Nobel Prize winner). Montagnier, then a researcher in the United Kingdom, perfected his own techniques, benefiting from the collaboration with Dubelco. He then set up a laboratory at Pasteur, and we know what happened next...

The exception does not prove the rule: it invalidates it, period. All S+ is the living proof and at least for itself, that RNA can be integrated... We know it, thanks to several Nobel prizes! This has not prevented the SPILF to perorate the contrary, and the agitation to take up again in heart, and cover itself with ridicule. It is here, and, frankly it would be funny if it did not show the weaknesses of our national Virology: pathetic!

CTCCTCGGCGGGCACGTAG ??? $#!+! Is there a Modernagate???


The case begins with a tweet from (@JikkyKjj) / Twitter.

But where does this #CTCCTCGGCGGGCACGTAG sequence come from? Here is what Alexandra says:
Well, that's jargon for us, so let's ask S. Bancel, CEO of Moderna... Here is his answer, on Fox at minute 7: 'the Wuhan laboratory may have made a mistake and may be responsible for it [...] Our scientists are checking. '. To be continued, then...

Genotoxicity


Didn't the FDA ask Pfizer for genotoxicity studies? Raoult and Alexandra warned you about the possible integrability of the code? We are still waiting! Well, a little less now that this in vivo study has been published: Intracellular reverse transcription of Pfizer BioNTech COVID-19 BNT162b2 mRNA in vitro in a human liver cell line.
Contrast this quote from an article in Le Monde in December 2020: 'Our current knowledge of how mRNA and the cell work is clear: mRNA vaccines cannot modify the DNA of human cells'. Well... It is advisable to abstain from speaking too quickly, to spread 'knowledge', especially when one does not have the least competence!

The proximal hypothesis... undermined...


The proximal hypothesis... This is the nice name that designates the hypothesis of the natural origin, in a word the bat that fucks a Pangolin... We don't hear many people defending it anymore! The uncovering of funding by the NIH, bypassing de facto the moratorium decreed by Obama, decreed because it is too risky, the refusal by DARPA (US Army) to fund Daschak's project, the persistent disappearance of the head of the Wuhan Lab (alias Batwoman), the famous furin cleavage site, etc, etc. That's a lot!

Baric explains here how to make money with a pandemic, and also the gain of function, also well explained by P. Daszak in this video

See this very complete study by Yuri Deigin and this excellent article by H. Banoun: The origin of the Covid-19 virus (in French)

The 'unfortunate' word by Bill Gates


Did his tongue slip? It's on YouTube, here
And to conclude that we will have to anticipate better, and be even faster.

Certainly, Bill... Once bitten, twice shy... For the poor 'fucked up' too, it will be necessary to anticipate better, and to be even faster!...

Weekly catch and 1/15


I'm making my 1/15 evolve: with my next dose, I'll go to 1/17... We'll see that next time.... Note that I feel less alone... Other almost-cured come to join us. We know of them thanks to a scientific publication.We will come back to them...

In the news...


- according to this opinion of the High Council of Public Health, of Jan. 11, 2022, available here:
You can't make this up!

- The swedish roulette: Here is the trick: you count the freshly vaccinated, recently infected (yes, it happens often, too often...) as unvaccinated. Doublepunch! We reduce the denominator, we increase the numerator and bingo! we create vaccine effectiveness ex-nihilo! Fenton (a probabilist...) had explained it, Marco Nius updated it. The idea is taken up by Pierre Chaillot (a statistician...) in an excellent humorous video, censored, but available here.

- The blog will become multilingual again: already the English version is catching up. It will soon be followed by the Brazilian version. I'm already considering a Spanish, Italian, etc. version.

- BREAKING NEWS: the article about Quatuor's results is published: it is here

Pieces of Anthology


This tweet from Prof. Molimard has aged very badly:
Oh, now I distrust pharmacokineticists (and those who foolishly echo them) like the plague! They are the kings of THE dose... But, as the Eclipse shows: THE dose is a lie! So, beware, beware...

A French genius


Pierre Sonigo is the father of your Pasteurian diagnostics and also of the Eclipse. We would like to see him again on this field! The video he delivers is remarkable for its clarity, intelligence and benevolence. If we want to understand what happened and finally put an end to the hysteria, if there is only one video to remember from this whole unfortunate affair, then we will go to his magnificent intervention at the Independent Scientific Council (ISC n°43: Immunity and Covid). It can be found on YouTube at minute 48.

As soon as we take into account the great omissions of the case: the circulating coronaviruses, the immunity acquired by children and those under 60 years of age, the erosion of this immunity, which is durable but not eternal, that it protects against severe forms of the disease but not against transmission, that it distorts the very notion of testing, that it makes it impossible to determine the right dose and the efficacy of the vaccine, we are dumbfounded. This is a great lesson for the future. The same applies to the Eclipse! Once we conceive it, once we observe it, we realize the ineptitude of THE dose, but also of mass trials. Since we don't all have the same Eclipse, we won't all have the same intermittency and there is a benefit in seeking to extend the Eclipse.

In another register, the famous Momotchi's(whose pseudonym, I humbly confess, I thought was hiding a HE electronic engineer, a HE and not a SHE) Cartesian, methodical analysis invited to leave France for Sweden is very impressive of clarity and calm. We discover her in this interview.

Finally, to open the minds and souls, this excellent choreography by Bintou Dembele: Les Indes Galantes - Dance of the Great Pipe of Peace. Great!

Feel free to comment, like, share and use

One believes to suffer to be cured, one merely suffers to enrich financiers... (inspired by Anatole France)

Wednesday, February 2, 2022

187


This was originally published here, in French (link).
We provide this translation for your convenience. Practical aspects may differ where you live.


4/7 in Italy! It's coming, it's coming...

By Charles-Edouard!

Very pertinent question, asked here:
What could be more natural than to think about it! When you see success rates of almost 100% in 4/7 for others, and a prolonged efficiency for yourself, you would like to think that limiting yourself to 5/7 would have been a missed opportunity. As it is iterative and Darwinian, the next increment is 3/7, it is obvious. This is not validated by a large clinical trial... So what??? it has not been invalidated either. If you don't even look for it, you can't find it!

The experimental method is described in FASEB-1: make sure of the good susceptibility of HIS virus (something that must have been done before initiating 4/7, so normally it's good), make sure of the efficacy at 4/7, don't try it under Isentress, Genvoya, Kaletra (but who still takes that?) monitor at the beginning by CV 1 month, 2 months, 4 months, 6 months (at the beginning only), and that's all! BIOLOGICAL follow-up necessary. The medical follow-up? Well... For the comfort of the mind? Maybe ? And still ... In any case, the medical follow-up in 3/7, did exist (100% success rate, subtracting the risk combos), and, in practice, it disappeared with Leibowitch...

What does the ANRS tell you? It could not be clearer: ' Get on with it
'...

A new publication in 4/7


This publication comes from Italy. We had distributed our biblio to various clinicians. Including them... Did it help? I don't know. We can see that French works are abundantly cited (ICCARE, Leibowitch, Calin, ANRS-4D, Quatuor). Normal, there are not many others (Breather, in 5/7, at most...). The results are the same: 100% success, a few dropouts... It's like usual... Nothing new... And the nothing new is reassuring!

The very interesting discussion is in the body of the text. That's why I made a translation in french, in extenso. You have to read it. There is a vibrant tribute to ICCARRE, despite a small inaccuracy: Leibowitch et al. published in 2010 (FASEB-1 and 2015 FASEB-2), BREATHER was published in 2016, so Leibowitch is earlier, not the other way around...


The dosages... They are instructive!


They made 4 dosages per patient... It is instructive, because as in ANRS 4-D, there are cheaters, and it shows! There seems to be 1 or 2 who take more, but mostly a dozen, or a third, who take less. And it works just as well! It shows us the way: 4/7 is good to start... It's a start... And, after a while, you have to grow up

The threshold dose is a joke!


The threshold dose is determined by the failures when introducing the molecule in a new therapeutic scheme. Never in the long term, never... I challenge you to find a threshold dose at T plus 1 year that is equal to that seen in the short term. The good example is Nevirapine, with its dose-dependent failures at less than 6 months(thanks to poor tolerability in some), but no failure beyond 8 months. No failures: no threshold.

The authors discuss here the doses observed after 3 days of interruption (but perhaps more, the patients were just doing their own thing), and we are successful even at values well below the IC90. Note that the 'official' therapeutic dose is 3 times IC90 for Rilpivirine, while it is 15 times IC90 for the more effective Dolutegravir. Look for the mistake...

The Eclipse exists: we see it, so what does the threshold dose mean? Moreover, in the long term, we don't know how to determine it. In the stable phase, it's just a flan!

Can do better...


I like this kind of publication: it is an obvious progress in the percolation of ICCARRE at the international level. This publication is in addition to the others. This poses 2 problems:

- as long as one perceives that the Eclipse is only a few days long, for everyone(vision of the 2000s), it is quite logical to consider the results of others for a reflection on oneself. Now that we have Eclipses that are both longer and more dispersed, these tests on others, on non-identical viruses, no longer make any sense!

- The tests accumulate ad nauseam. Medical Darwinism obliges, it is only a question of time that we pass to 3/7... And what a waste of time! Obviously, if 4/7 is as 'good' as 7/7, it is no less 'bad'.

The 'enemy' of yesteryear was 7/7(will there still be people to practice it in a few years?). It has fallen. The new 'enemy' is the 4/7: it will necessarily fall one day...

In the news


- Satoshi Omura, Japanese Nobel Prize winner, presents I*T as a treatment against C*D: no doubt, a Nobel Prize is no match for 'fax checkers' without the slightest scientific background. It should be noted thatin vitro I*T is as effective on Omega as on the others...

- Before/After critical analysis of the pasteurian 'predictions', it's here, and it's scouring! (it's good too...)

- Very well documented article by Helene Bannoun: The origin of the Covid-19 virus

- Very interesting Evaluation of the methodological methodological practices implemented in Pfizer trials, by Christine COTTON

- Genetic Forcing, Self-Disseminating Vaccines, Chimeric Viruses... The sorcerers' apprentices of the genome by our excellent Bruno Canard, Étienne Decroly Jacques Van Helden (it's not free, but if you ask nicely...)

Pieces of Anthology


- The virus has not mutated,' says Professor Karine Lacombe on RTL (at 4 min 50 sec): To be enjoyed in moderation!

- Typhus, a little history on Science.org:

The French genius


Today is Saint Darwin's day! It was Lamarck who discovered Evolution. Darwin, the Evolution under pressure from Selection. This is still relevant, even if many advances have been made since then. Our French genius is Montagnier, who died on February 8.
If he had not set up the Pasteurian Laboratory on Oncoviruses, there would not have been the very lucrative patent, there would probably not have been Barré Sinoussi or Schermann at the head of this world competition. There would have been a genius, but not French...

We don't care about the rest, the squabbles, the greatness and the smallness. Read again Darwin, Descartes or Newton, it's not all rosy either; they also said some bullshit with no equal; history will sort it out.

The fact remains that for us, Montagnier was the beacon of a whole generation! In fact, I am interested in 2 concepts that he exposed:

- DNA does not integrate randomly anywhere (so depending on where it is integrated, it will be more or less active)

- silencing(passive reservoir) is a reasonable therapeutic goal(as for tuberculosis)

We will come back to this, it is inevitable, since it is our salvation...

Feel free to comment, like, share and use

Turn off the TV and don't be fooled by Pharisee venality


Tuesday, February 1, 2022

186-1


This was originally published here, in French (link).
We provide this translation for your convenience. Practical aspects may differ where you live.


We will miss Professor Luc Montagnier!

By Charles-Edouard!

Prof. Montagnier has left us: it is very sad


I had planned in my posts in preparation (The Saint Darwin 2022, the Italian 3/7), a paragraph "French Genius" dedicated to Pr. Montagnier. During his last public intervention (Parliament of Luxembourg) he seemed so weak that I considered a tribute during his lifetime. If you want to tell people that you admire them, you might as well say it when they can hear it.

Reality catches me off guard. France Soir, historically a newspaper of resistance fighters, is rejuvenating itself and announces his death on February 8th. My sorrow is immense, my gratitude too. My soul is sad and I have read all his books... Including recently, a video (already cited, it is here) left us a milestone on the path we can follow. He talks about what we can aim for in terms of healing.

The Charles-Edouardian thought, the only one to have ever led to near healing, was reinforced by his insights. We shall discuss further the fact that insertion into the reservoir is not random and that we can hope to encyst the Monster, if not eliminate it. Montagnier was faster than we were, and to understand what he said requires time to reflect. We will come back to this...

At the time of writing, the AFP has not yet deigned to inform you. The search for "AFP + Montagnier", in the news tab, does not return anything, for the moment. Let's bet that they will end up announce the death of one of our national pride. We will see, we will judge...

In the meantime, let's come back to what Montagnier was able to explain and which sheds light on our vision of a possible therapy, one can gladly indulge in the sadness of having lost a beacon of lucidity in an ocean of mediocrity.

186


This was originally published here, in French (link).
We provide this translation for your convenience. Practical aspects may differ where you live.


4/7 in Italy! It's coming, it's coming...

By Charles-Edouard!

Very pertinent question, asked here:
What could be more natural than to think about it! When you see success rates of almost 100% in 4/7 for others, and a prolonged efficiency for yourself, you would like to think that limiting yourself to 5/7 would have been a missed opportunity. As it is iterative and Darwinian, the next increment is 3/7, it is obvious. This is not validated by a large clinical trial... So what??? it has not been invalidated either. If you don't even look for it, you can't find it!

The experimental method is described in FASEB-1: make sure of the good susceptibility of HIS virus (something that must have been done before initiating 4/7, so normally it's good), make sure of the efficacy at 4/7, don't try it under Isentress, Genvoya, Kaletra (but who still takes that?) monitor at the beginning by CV 1 month, 2 months, 4 months, 6 months (at the beginning only), and that's all! BIOLOGICAL follow-up necessary. The medical follow-up? Well... For the comfort of the mind? Maybe ? And still ... In any case, the medical follow-up in 3/7, did exist (100% success rate, subtracting the risk combos), and, in practice, it disappeared with Leibowitch...

What does the ANRS tell you? It could not be clearer: " Get on with it
"...

A new publication in 4/7


This publication comes from Italy. We had distributed our biblio to various clinicians. Including them... Did it help? I don't know. We can see that French works are abundantly cited (ICCARE, Leibowitch, Calin, ANRS-4D, Quatuor). Normal, there are not many others (Breather, in 5/7, at most...). The results are the same: 100% success, a few dropouts... It's like usual... Nothing new... And the nothing new is reassuring!

The very interesting discussion is in the body of the text. That's why I made a translation in french, in extenso. You have to read it. There is a vibrant tribute to ICCARRE, despite a small inaccuracy: Leibowitch et al. published in 2010 (FASEB-1 and 2015 FASEB-2), BREATHER was published in 2016, so Leibowitch is earlier, not the other way around...


The dosages... They are instructive!


They made 4 dosages per patient... It is instructive, because as in ANRS 4-D, there are cheaters, and it shows! There seems to be 1 or 2 who take more, but mostly a dozen, or a third, who take less. And it works just as well! It shows us the way: 4/7 is good to start... It's a start... And, after a while, you have to grow up

The threshold dose is a joke!


The threshold dose is determined by the failures when introducing the molecule in a new therapeutic scheme. Never in the long term, never... I challenge you to find a threshold dose at T plus 1 year that is equal to that seen in the short term. The good example is Nevirapine, with its dose-dependent failures at less than 6 months(thanks to poor tolerability in some), but no failure beyond 8 months. No failures: no threshold.

The authors discuss here the doses observed after 3 days of interruption (but perhaps more, the patients were just doing their own thing), and we are successful even at values well below the IC90. Note that the 'official' therapeutic dose is 3 times IC90 for Rilpivirine, while it is 15 times IC90 for the more effective Dolutegravir. Look for the mistake...

The Eclipse exists: we see it, so what does the threshold dose mean? Moreover, in the long term, we don't know how to determine it. In the stable phase, it's just a flan!

Can do better...


I like this kind of publication: it is an obvious progress in the percolation of ICCARRE at the international level. This publication is in addition to the others. This poses 2 problems:

- as long as one perceives that the Eclipse is only a few days long, for everyone(vision of the 2000s), it is quite logical to consider the results of others for a reflection on oneself. Now that we have Eclipses that are both longer and more dispersed, these tests on others, on non-identical viruses, no longer make any sense!

- The tests accumulate ad nauseam. Medical Darwinism obliges, it is only a question of time that we pass to 3/7... And what a waste of time! Obviously, if 4/7 is as 'good' as 7/7, it is no less 'bad'.

The 'enemy' of yesteryear was 7/7(will there still be people to practice it in a few years?). It has fallen. The new 'enemy' is the 4/7: it will necessarily fall one day...

In the news


- Satoshi Omura, Japanese Nobel Prize winner, presents I*T as a treatment against C*D: no doubt, a Nobel Prize is no match for 'fax checkers' without the slightest scientific background. It should be noted thatin vitro I*T is as effective on Omega as on the others...

- Before/After critical analysis of the pasteurian 'predictions', it's here, and it's scouring! (it's good too...)

- Very well documented article by Helene Bannoun: The origin of the Covid-19 virus

- Very interesting Evaluation of the methodological methodological practices implemented in Pfizer trials, by Christine COTTON

- Genetic Forcing, Self-Disseminating Vaccines, Chimeric Viruses... The sorcerers' apprentices of the genome by our excellent Bruno Canard, Étienne Decroly Jacques Van Helden (it's not free, but if you ask nicely...)

Pieces of Anthology


- The virus has not mutated," says Professor Karine Lacombe on RTL (at 4 min 50 sec): To be enjoyed in moderation!

- Typhus, a little history on Science.org:

The French genius


Today is Saint Darwin's day! It was Lamarck who discovered Evolution. Darwin, the Evolution under pressure from Selection. This is still relevant, even if many advances have been made since then. Our French genius is Montagnier, who died on February 8.
If he had not set up the Pasteurian Laboratory on Oncoviruses, there would not have been the very lucrative patent, there would probably not have been Barré Sinoussi or Schermann at the head of this world competition. There would have been a genius, but not French...

We don't care about the rest, the squabbles, the greatness and the smallness. Read again Darwin, Descartes or Newton, it's not all rosy either; they also said some bullshit with no equal; history will sort it out.

The fact remains that for us, Montagnier was the beacon of a whole generation! In fact, I am interested in 2 concepts that he exposed:

- DNA does not integrate randomly anywhere (so depending on where it is integrated, it will be more or less active)

- silencing(passive reservoir) is a reasonable therapeutic goal(as for tuberculosis)

We will come back to this, it is inevitable, since it is our salvation...

Feel free to comment, like, share and use

Turn off the TV and don't be fooled by Pharisee venality

Saturday, January 1, 2022

185


This was originally published here, in French (link).
We provide this translation for your convenience. Practical aspects may differ where you live.


Isobolograms and the ineptitude of the single dose

By Charles-Edouard!


Isobologram: oral vs. injected dose


For those who practice ICCARRE-Premium (1/7 or better) the question of dose is subsidiary. With injectables, for the others, the question of the dose comes back, with an extreme acuteness: overdose guaranteed for 95% (or more) of the patients.

One of the arguments in favor of unnecessary (or even deleterious) overdosing is that many patients take their daily medication incorrectly. This is probably more pronounced in countries where supply is variable or even random (e.g. Maghreb). Okay, okay... Let's go for a 'regulatory' argument but what about the metronome patient? Does she have to dose every day, because Algerian women or others have problems to get supplies? Should she fill herself up daily with the pretext that the homeless desocialized, abandoned, are more and more numerous, and have real problems?

Another argument can be proposed: the variable bioavailability: it is, for example, notably problematic for Raltegravir for which Merck will have made the galenic 3 times!(At the end, they went as high as ... 1200 mg/d !!! And it was authorized! - To my knowledge, nobody takes it - ...): we inflate a little, because well... You never know... Especially since we don't want to know... With injectables, this argument is not valid anymore!

A single dose without taking synergies into account


Leibowitch kept coming back to the famous synergies, without any real further explanation. It's not that complicated. Take an antiviral A and an antiviral B, when you use both you can have an antagonistic effect (A + B is less than the expected sum of the effects), a purely additive effect (A + B gives the expected sum of the effects) or a synergistic effect (A + B does better than expected). Apart from any pharmacokinetic consideration...

Ritonavir improves intake by a known pharmacokinetic effect of slowing down hepatic metabolism: it is not a synergistic effect.

When La Scola (Raoult team) shows in vitro that HCQ + AT works better than the simple sum of the effects, it is synergy: there is no pharmacokinetic role (e.g. metabolism by the liver) in a test tube... On the other hand, there is no synergistic interest to put 2 NNRTI (ex. NVP, EFV, RPV) in a combo...

However, if we look carefully, the usual dose of a molecule is a unique value, which NEVER takes into account what we put with it.(there is at least one recent exception: do you see it?...).

What is an ISOBOLOGRAM?


Ah well... It's easy to understand!... It's like Isotherms or Isobars: we draw the curve of same efficiency by varying the dose of each component. The diagonal is the neutral curve: on it the effects of the products are added, simply. As for Dalton's law for gases: the total pressure of a gas mixture is equal to the sum of the partial pressures. One mixes, it adds, no more no less. If the curve is in the SYNERGETIC range, less A and less B are needed to obtain the added effect of A and B. On the contrary the curve can be in the ANTAGONIST (= ANTI-SYNERGETIC) area, in this case you need more A and B when mixing A and B to obtain the same combined effect.

A now famous example of SYNERGY is the addition of HCQ to Azithromycin, at usual doses, which is much more effective in neutralizing SARS-Cov2 than HCQ or AT alone: this is why the idea defended by G. Pialloux was stupid, i.e. to test HCQ alone! The guys are czar infectious diseases specialists, but SYNERGY ?? They don't get it... Yet it is a great classic for... Tuberculosis or malaria... Of course, this is done in vitro. In real life, you might have to test a bit, but at least it's a guide.

Efavirenz-Entricitabine (Atripla ™) isobologram:


In Atripla ™ we find the STANDART dose of Efavirenz (600 mg) plus the STANDART dose of Entricitabine plus the STANDART dose of Tenofovir. I give you a first Isobologram, where you can clearly understand the ineptitude of the thing!

We have no scruples to say that it is completely stupid! Since the ENCORE1 trial has proven that 400 mg is as good (or even better...) than 600 mg. We know that! Sponsored by Bill Gates... The Morlat report endorses this alternative... The 400 mg combination drug exists (Mylan). But... But... It is not marketed in France.

Look for the mistake! We'll see all this next time...

Weekly intake, 1/15 and treatment obligation


January 24th is my freedom day! Phew, it's over... The 1/15 means 24 doses a year, no more! It's an important day. Well...

Instead of pissing them off, we should give a medal to all those who have gone through 2 years of pandemic without getting sick even once!

Everyone will have understood what is coming next in terms of public health and that injectables, QR codes and other technological prowess will promote.

I keep well far away and the obligations suffered in France and elsewhere amaze me. And I find it very sad...

In the news


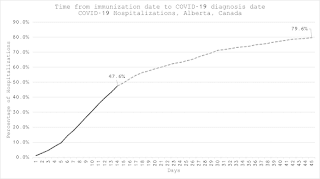
- I had quoted Pr. Fenton's intriguing post: The delay of 2 (or even 3) weeks between the injection and the validation of vaccination would not distort too much the efficiency if it wasn't for the ADE. Canadian statistics (Alberta): 50% of Covid cases occur within 2 weeks of the 'protective' injection. Not only are these people not counted as vaccinated, but they are counted as non-vaccinated, which they are not... Kiss Cool effect guaranteed on the efficacy ratio. We reduce the denominator, we increase the number and there you go! 95% efficiency on the counter... Except that the counter is a TV commercial...

- Along the same vein: DRESS (a French governement statistics body). Not knowing how to extract the vaccination status of all, it allocates the unknown cases between vaccinated and non-vaccinated according to a fanciful distribution key but favorable to the vaccine: vaccinated people are counted as non-vaccinated: and tada! We should say: not knowing, we don't count them, but here, we count them in the category that 'suits' our narrative best. Except that it is obvious and it looks ugly!

- Marco Nius makes an amazing simulation. On a small number of people, a marginal error in classification is enough to increase the relative risk from 1 to ... 5!


Feel free to comment, like, share and use

Turn off the TV and don't be fooled by the Parisian venality

Thursday, December 2, 2021

184


This was originally published here, in French (link).
We provide this translation for your convenience. Practical aspects may differ where you live.


Mono-Cabotegravir: it makes sense!

By Charles-Edouard!

Read right here, in the discussion ...

Knock on wood... That is to say, hoping that it will hold up against all odds? At the beginning, in 6/7, I was a bit nervous. Knowing where The Monster is, at D+27 in my case, knowing if he has a reservoir lair), disappeared in my case, it helps to live confidently, without even touching wood. We can consider 2 approaches: Eclipsotherapy (measuring the Eclipse, then adjusting the tempo, or cautious advance, under frequent CV, at the beginning, starting with 2/8... This is how I discovered my new mode...

The Right Dose: a promise never kept


Overdosing does not happen by chance: it is imposed, among other things, by the emergency. ARVs, when combined, can do more than add up. By synergy, 1+1 = 3 or 4 or...10. Synergy will apply to A+B (e.g. HCQ+AT), but not to A+X. The Zotorities, (in fact, only the FDA counts) were considering an adapted dosage, reflecting the synergy. That's good, that's legitimate, but in a hurry... The pressure was on for a "let's see what happens next".


It's understandable. The promise is legitimate... The labs are doing their jobs, each one on its side, proposing the maximum dose, without even trying to position themselves on an optimum of efficiency, cf RAL, EFV, and so on, the Zotorités have done theirs: authorize, and behind... Behind... The medical profession is absent! Patients you have been betrayed! Betrayed by whom? The medical profession which has failed to keep its promise and its self-proclaimed deontology of not doing (too much) harm!

They did not do the job! Period! Some of them have tried a little, the Fauci, Leibowtich, Katalama, A. Calmi, with more or less intelligence and more or less perseverance. The associations have seen their members change, the initial pugnacity is lost: nobody cares and the victim is you! Doubly... Firstly because the overdose is never a plus in terms of health, and also because the billion Euros thrown out of the window, it is as many relocations, unemployment and social suffering!

Overdosing: EFV, NVP, RAL and the ultimate... DTG


In a famous article, A. Calmi gives some historical examples. Alaxandra, why stop in such a good way? Why offer the dosage only to patients who do not tolerate it well, as if toxicity was limited to intolerability.

The most devastating drug is Efavirenz. First, because its tolerability is so poor. Secondly, because the shameless dose of 600 mg has finally been replaced by 400 mg (see WHO). Ah yes... Replaced in the USA and in countries that depend on American aid... Yes, today we have better combos in Kinshasa than in Paris. It's to die of overdose! Finally, because the phase 2 trial did indicate 200 mg as the dose to be retained. Even worse, this trial, which is supposed to protect against overdose, was done at 200, 400 and 600 mg. 200 mg was the lowest dose tested. So to know the dose to be retained, it would have been necessary to (re)test lower. A theoretically favorable value is ... 60 mg (in combination with TDF/F-3TC), but it has not been tested!

RAL is a real galenic disaster: the manufacturer is on its third galenization! In the UK, the reference treatment is RAL 1200 mg + ABC 600 mg + 3TC 300 mg, PER DAY! It's crazy! And people are taking it! Without question ???

NVP is a lot of nonsense! Even in Bichat (Peytavin ?) we realized it! That's how obvious it is! The bioavailability of the prolonged form (XR, in 1 tablet) is such that the dose in fine is 4 times less than the ANRS threshold dose, and it works. This dose is reached with a single standard 200 mg tablet. The ANRS threshold dose has not been corrected for this. So we have publications with NVP 200 mg + 3TC 300 mg, without concern. Note that patients who take 400 mg embedded in a plastic foam only receive 200 mg, so they do not realize it but their dose has been reduced de facto. The fact remains that this drug is too expensive and moreover it is not beautiful to see!

The worst of the worst is DTG: 15 times the IC90! Only that!

DTG is overdosed: CTG is the proof


The FDA distinguishes 3 types of patients: the newcomers(the naive, so aptly named), the experienced(yes, yes, they do participate in full-scale experiments) in success, the experienced in failure: If we propose a pharmaceutical formulation to these patients in despair, it is the MA assured, without discussion. This is normal. For the latter, it is 100 mg/d. Well... let's not quibble, that's the dose used for rescue, in a perilous situation. At the usual rate of ... 1200 Eu/month, it is classic, shocking but classic. The others? Well, it's less. But not less turnover, right? I'm a big Pharma who just saved your ass, so be nice. 600 Eu/month is the usual rate. And by simple rule of three, for 600 Eu/month, you will get 50 mg. Is it useless? But we don't care: we have to save ViiV from bankruptcy (all their drugs are in the public domain).

So we give 50 mg to people who don't need it. Who doesn't need it? People who have a susceptible virus? Who is susceptible to a susceptible virus? People who are genotyped seriously (or even phenotyped) and people who are successful. So, in these people, yes! we can lower the dose, even to the reasonably acceptable dose in the phase 2 trial, i.e. 10 mg of DTG. But we, the chemists stuffed with $$, have something better! We will give you the same corkscrewbut change the handle. We change the name, the thing, we redo the studies, we drown the fish poison and... We change the dose(of the same corkscrew)... And... The target population.

We fire the Trojan horse, the failed patients, the few who have allowed us to stuff the whole planet, and us (in $$) at the same time. Read the HAS, here: right on target:
In these patients, 50 mg DTG is 15 times (15 times!!!) the IC90. With CTG, at 30 mg, it will be 2 times less corkscrew (technically we say pharmacore), that is 7 times the IC90 . And it is indeed the ideal IC90, since we have selected the susceptible patients. So even 30 mg seems huge!

Mono-DTG works on susceptible viruses and serious patients


There is a wonderful Swiss trial with 100% success (try to do better!). Lanzafame published its results on patients, without too restrictive screening, it also works if you follow the protocol well. Once people have proven that the virus is not twisted and that they know how to follow the protocol, one wonders why on earth they should stay at 50 mg!

I did Mono-DTG 1/2 pill (6 months) then Mono-DTG 1/4 pill (6 months), in 7/7, with no worries, no failure, no resistance acquired, nothing, Nada. To me, I should not be offered VOCABRIA... With my experience of Mono-DTG 12,5 mg (7/7), I will always go for MONO-CTG 7/7, just for fun.

Mono-CTG injection: it looks good...


Good compliance is key to success with Mono. And what better way to measure and guarantee compliance than with injections? It is not easy to hide or minimize non-adherence with injections... So, then... Well, that's for another time! Subscribe now!

The orphan virus is making babies


- Will mass vaccination, with a mono-centric strategy, prove to be a big mistake? I doubt that history will ever judge it. The West has been living for 2000 years in a macabre, obsolete hysteria... And the inventory of this millennial error is still pending. Is vaccination reversible? In general, no... For a real vaccine, it is not... But here? Antibodies have a limited lifespan, it is a chance to seize! Also if your virus acquires resistance, you have the choice (if you are allowed to...) between overdosing and drowning. You have to make a choice and beware of resistance breeders. While we can, drowning is my strategy of last resort. Sonigo has been explaining for a long time that from evolution to evolution, the virus should become more contagious AND less virulent. P. Sonigo gave an excellent interview. Geert Vanden Bossche explains here, in French, that the succession of waves indeed favors contagiousness, but that there is no apodictic necessity for less virulence. I had said, at the beginning, that a selective strategy of Covidization of the youngest would be possible. Now on the table: omicronization of the injected...

The false witnesses and their obliged accomplices


Francis Palombi will have admitted having deceived the journalists of BFM, at the time of a shooting at the hospital of Neuilly Ambroise Pare. Caught red-handed, he declares: Bad comedian certainly. Sincere at least. I assume my convictions. Did BFM let itself be trapped? Or has seized the opportunity to stage the convictions of... BFM. The debate on intermittence will have been polluted by false testimonies AND those who allowed them. This is important: the responsibility of the false witnesses exists, but the responsibility of the media who carry an intention, even a conviction, is even greater.

In the news


- I had pointed out Fenton's post, here is the interview he gave (and which disappeared quickly...). Beyond this controversy, his blog addresses a very interesting issue: the assessment of risk by the Bayesian method

- two articles of great importance for us: A possible sterilizing treatment for HIV-1 infection without stem cell transplantation and Distinct mechanisms of long-term virological control in two HIV-infected individuals

- Links disappear with time... My new MegaArchive keeps this blog in-extenso as well as all the resources, including video: nothing will be lost anymore...

- Happy Holidays !!!

Feel free to comment, like, share and use

Turn off the TV and don't be fooled by the Parisian venality

Wednesday, December 1, 2021

183


This was originally published here, in French (link).
We provide this translation for your convenience. Practical aspects may differ where you live.


A giant step towards recovery and that's me!

By Charles-Edouard!

My tank has disappeared... or... did I make my tank disappear?


As long as you give a prize (INSERM) or a lot of $$, it would be nice to do it for a real real ization. And, to give to those who do. Not to the spectators! The spectators watch, amazed, admire and... Applaud!

Without further ado I reveal where I stand, and we discuss it afterwards. My tank is measured every year: 2015, 2016, ... 2018. Low but present, unequivocal. 2019 and 2020: three attempts where the lab said they were unable to do the measurement. 2021: the laboratory confirms the undetectability: it is without appeal: something happened!

And this something is huge: the disappearance of the tankit's gone under the radar! Now, if you find even one doctor capable of showing such a masterful Before-After, just let me know: I have never seen one: it is the GRAAL of the grail: no one has ever managed to do it, except by genetically modifying the individual and perhaps in the Biosantech trial (to be verified...). You know how to do this, you are part of the Kador, the STARS. And if you don't know how, well, you are not a STAR.

We are talking about DNA(measurement of the reservoir according to the ANRS method) and not RNA(whose undetectability is maintained by the ICCARRE+ method)

Under the radar! it is under the radar...


When the numbers are low, the validity of the results is questionable... Yes, yes, yes... And we'll do it again in 2022(if this stupidity of sanitary pass has ended, if not, we'll do it later, or elsewhere... ). I'm not worried or in a hurry... from 2015 to 2018, the lab was able to come out with results, but not in 2019 (twice...) we suspected something! Again in 2020... These are background noise problems: the signal is drowned in a small hubbub. So for 2021, I used a little trick (that I got from Ananworanwich) to try to get the signal back to the best I could dream of. Who knows... But at least the machine spit out something! It spit out ZéRo, and that's not nothing!

When does it go under the radar?


Good question... First, when it was above the radar, it was for real. How do we know? because several months before the last 'positive' reading, I had a (very) high RNA reading (at that level of CV, it's not a blip!). This virological failure, frankly, will have been recovered with brilliance, and above all, a few months after the incident, the reservoir was as usual, in conformity with the classical observation that a short period under active viremia does not affect the reservoir level.

So moving the tank, one way or the other, is no small feat! You make a controlled slip and it doesn't change your burden. The alla Pharisee argument that intermittency (or even failure) would make the tank go up (boo!...) is at odds with what we know. There is no need to worry unnecessarily...

I think that the passage under the radar dates from 2019, and that 2021 is only a confirmation. Besides, after 3 unsuccessful readings, we could have already ruled. And all these impossible or null measures, are in a series that starts in 2019 and interrupts an earlier series of remarkable consistency!

No more reservoir? What's the point? What to do next?


As long as you have a tank left, there are a lot of questions that don't arise! Nobody asks them... And when you don't have a tank anymore, everything comes up: you are in terra incognita! So, we'll see about that next time

Obligation of treatment / Judiciarization


When a virus comes from nowhere and appears 800 m from the only laboratory in the world working on these living viruses, we say that a pangolin has been killed by a bat. When a variant appears without any known recent emergence (despite 2 million genotypes!) we immediately find the source: an S+ patient with uncontrolled HIV... Oh well... The use of some mutagenic molecule? No ? Really? No? Well... If you say so. Of course, there were some who immediately decried the situation and wished it would end: hear, hear !

In the news


- Raoult said he reviewed a forthcoming article on a very large prophylaxis study at HCQ... Hi... Hi... He knows the result... Do you? Not yet... He seems quite confident about the future, don't you think?

- In the meantime, a large prophylaxis study with VMI confirms, not surprisingly, that it has a role to play!

- Merck announces that it has stopped its Islatravir study in 1/7, under a pretext as futile as it is unverifiable. Let's keep an eye on Merck's next announcements on Islatravir. I bet that they did not hang up their apron and that the others finally gave in in the negotiations... Merck's initial objective was always injectable. The oral form in 1/7 was only for as long as there was no injectable solution... And if the injectable that we feel is coming does not work, there will always be time to come back to 1/7, but in IRT, this time, as it would have been reasonable to do from the start... We'll see... The saga continues, and we will come back to it.

- bad luck: Pasteur (Lille) interrupts its clinical trial... For lack of patients! In the middle of the e-ieme wave! You have to do it!!! it's here. By dint of being soaped the board, it wears out!(Even Pasteur... Apart from laying down algorithmic elucubrations that leave one quite perplexed...)

- Pr S. Gayet is an infectiologist who seems to deal with nosocomial diseases in hospitals (of which Covid is a part...). Behind his phlegm and his Alsatian accent, he says exactly the same thing as Raoult. It is less brilliant, less striking, but it is kif and it is here.

- A stellar article by Norman Fenton, who notes a wave of deaths, NOT Covid, among NON-vaccinated people, coinciding with the (NON)vaccination campaign, whereas this campaign is, for them, a NON-event! The (non covid) deaths of the freshly vaccinated (side effect: death...) have been attributed... to the cohort of the ... NON-vaccinated. So, of course, when you correct the bias, it looks bad. It's a bit hard to read and it's here.

Feel free to comment, like, share and use

I'm walking against the current, because I don't know how to walk against my heart...